Recurrent Shoulder Dislocation Treatment in Bengaluru
A shoulder that repeatedly slips out of place can affect confidence, movement and everyday activity. Specialist assessment can help identify the cause of instability and determine whether rehabilitation, activity modification or shoulder stabilization may be appropriate.
Book a Consultation
Tell us what you are experiencing. Our team will contact you regarding your appointment.
Our orthopaedic coordination team will contact you regarding your appointment slot.
What Does Shoulder Instability Mean?
The shoulder is the most mobile joint in the human body. Because the ball is large and the socket is shallow—similar to a golf ball sitting on a tee—it depends on a complex ring of cartilage (the labrum), surrounding ligaments, and rotator cuff muscles to stay securely centered.
Dislocation
The ball (humeral head) moves completely out of the socket (glenoid). It typically requires physical reduction by an orthopaedic doctor or emergency team to be restored to position.
Subluxation
The ball partially moves out of its normal position and slips back into place on its own, producing an acute popping or slipping sensation followed by temporary numbness or ache.
Instability
A chronic state where the shoulder repeatedly feels as though it is slipping, shifting, or giving way during routine daily arm motions, gym workouts, or sporting activity.
Signs of Shoulder Instability
Shoulder instability can present in different ways, from dramatic recurrent dislocations to subtle feelings of apprehension when raising the arm.
Repeated Dislocation
The shoulder has slipped completely out of place more than once, often occurring with progressively less trauma than the initial injury.
Feeling of Slipping
A loose sensation that the ball is slipping or sliding across the socket edge, especially during sudden directional arm shifts.
Apprehension
Sharp discomfort, hesitation, or fear during certain arm postures—particularly when the arm is positioned overhead and rotated outward.
Shoulder Pain
Persistent aching or sharp discomfort following an instability episode, often accompanied by local swelling or muscle spasm.
Weakness & "Dead Arm"
Temporary numbness, tingling, or weakness after a subluxation episode, leaving the arm feeling heavy, tired, or unreliable.
Reduced Confidence
Patients actively avoid sports, gym workouts, swimming, or sleeping in certain positions because they worry the shoulder will dislocate again.
Clinical Insight: Recurrent instability can have different causes. A specialist assessment helps determine which structures—such as the labrum, joint capsule, or bone rim—may be involved.
Get Your Shoulder AssessedWhen Should a Recurrent Dislocation Be Evaluated?
A shoulder that dislocates repeatedly is at risk of progressive labral detachment or bone loss. Specialist evaluation is appropriate when:
How Is Shoulder Instability Diagnosed?
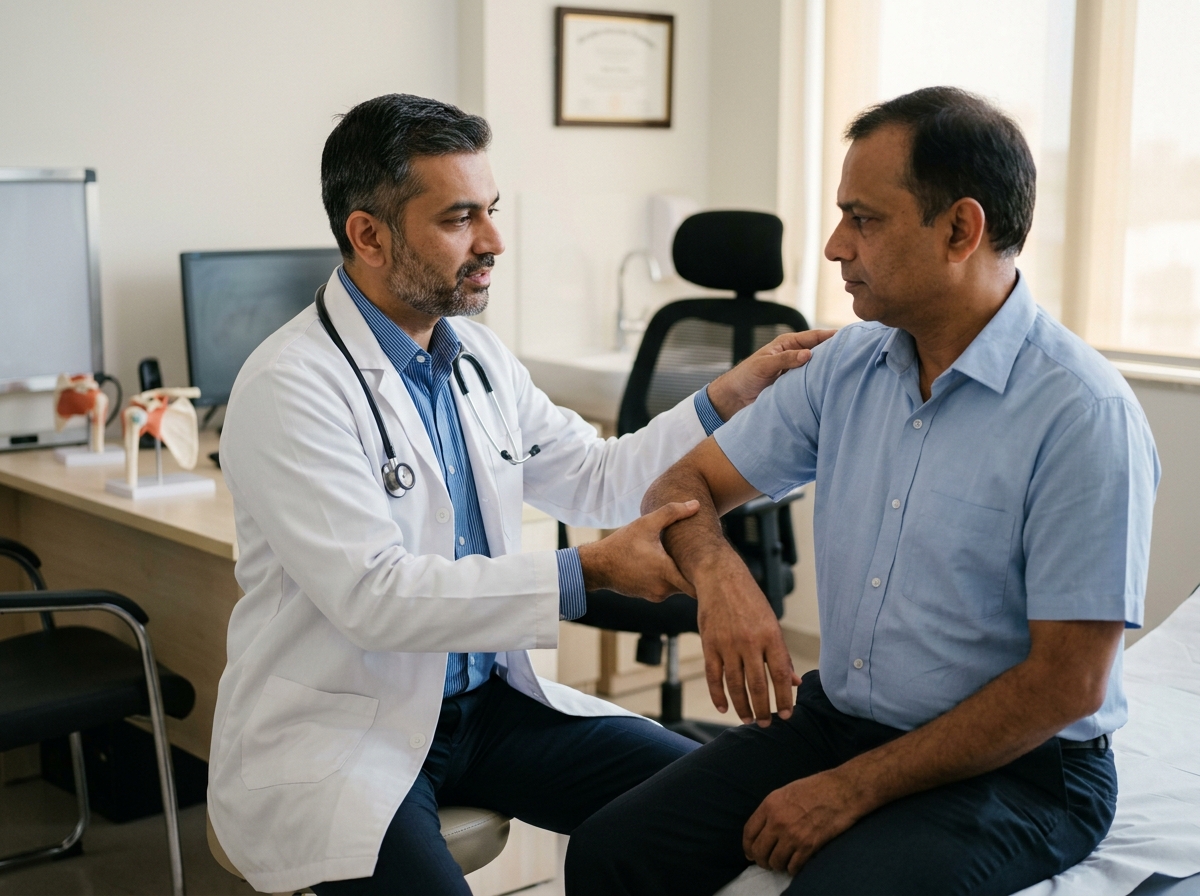
A comprehensive diagnosis combines detailed clinical examination maneuvers with dedicated shoulder imaging when clinically indicated.
1. Clinical Examination
During clinical evaluation, the orthopaedic specialist assesses:
2. X-Ray & MRI Imaging
Specialized X-rays (such as true AP and axillary views) assess joint alignment, verify that the joint is properly reduced, and screen for bone fractures or socket rim defects.
MRI or MR Arthrography is used when clinically indicated to directly evaluate the cartilaginous labrum, capsular tissue, rotator cuff tendons, and quantify any bone loss on the socket or ball.
Bring previous X-rays, MRI scans or reports to your consultation so the orthopaedic specialist can review the findings together with your symptoms and physical examination.
Book Shoulder Imaging ReviewWhy Can a Shoulder Dislocate Again?
Recurrent instability occurs because an initial traumatic dislocation can tear or stretch the structural restraints that hold the joint together.
Labral Detachment
The labrum (fibrous bumper) tears away from the socket rim during trauma and may fail to heal back in its anatomical position, leaving a path for the ball to slip forward.
Capsular Stretching
The fibrous joint capsule and glenohumeral ligaments stretch during forced dislocation, creating permanent tissue laxity that reduces passive restraint.
Bone Defects
Repeated dislocations can chip or erode the anterior socket rim (glenoid bone loss) or cause a dent in the back of the humeral head (Hill-Sachs lesion).
What Is a Bankart Lesion?
A Bankart lesion is one of the most common structural injuries that may occur following an anterior shoulder dislocation.
Understanding the Bankart Injury
The glenoid labrum is a rubbery ring of tissue that deepens the shallow shoulder socket. When the humeral head is forced forward and out of the socket during an anterior dislocation, it tears the labrum and attached inferior glenohumeral ligament from the lower-front (anteroinferior) margin of the bone.
- Soft-tissue Bankart: The labrum tears cleanly from the cartilage margin.
- Bony Bankart: A small fragment of the glenoid bone breaks away with the labrum.
Clinical Significance
Because the labrum acts like a doorstop preventing the ball from rolling over the edge, an unhealed Bankart lesion significantly increases the likelihood of recurrent giving way or repeated dislocations, particularly in young or active patients.
Other Injuries Can Accompany Shoulder Instability
Dislocation forces affect multiple structures around the shoulder. An accurate evaluation checks for accompanying joint findings:
Hill-Sachs Lesion
An impaction indentation on the posterior-lateral aspect of the humeral head that occurs when the ball impacts the hard edge of the socket during dislocation.
Glenoid Bone Loss
With repeated dislocation episodes, the front edge of the socket can chip or wear down, reducing the surface area available to support the humeral head.
Labral Tears (SLAP)
Damage can extend to the top of the labrum where the biceps tendon attaches (SLAP lesion), producing clicking, catching, or deep anterior shoulder pain.
Rotator Cuff Injury
In patients over 40 years of age, a traumatic shoulder dislocation can simultaneously tear the rotator cuff tendons (particularly the subscapularis or supraspinatus).
Capsular Laxity
Generalized stretching of the joint capsule and surrounding ligaments that allows excess translation of the humeral head in multiple directions.
Does Every Shoulder Dislocation Need Surgery?
Treatment depends on age, number of dislocations, cause, activity level, sport requirements, structural injuries, bone loss, shoulder stability, response to rehabilitation, and patient goals.
Non-Surgical Management
May be appropriate in selected patients, particularly following a first-time dislocation in older individuals, patients with low physical activity demands, or non-traumatic laxity.
Management may include:
-
Brief Immobilization: Resting in a sling for a short period to allow acute inflammation to settle.
-
Activity Modification: Avoiding vulnerable abducted, externally rotated arm positions.
-
Targeted Physiotherapy: Specialized shoulder rehab guided by hospital therapists.
-
Rotator Cuff Strengthening: Building dynamic muscular compression across the joint.
-
Neuromuscular Control: Retraining proprioception and joint position sense.
-
Gradual Return to Activity: Phased progression based on stability criteria.
Surgical Stabilization
May be considered in selected patients, particularly those with recurrent episodes, structural labral detachment, young contact athletes, or significant functional limitation.
Considerations May Include:
-
Recurrent Dislocation Episodes: Shoulder repeatedly dislocating during daily life or sport.
-
Confirmed Bankart Lesion: Detached labrum failing to maintain socket depth.
-
Young, Active Contact Athletes: Higher statistical risk of recurrence without anatomical repair.
-
Bone Rim Loss: Assessing whether soft-tissue repair or bone augmentation is needed.
-
Failure of Non-Surgical Care: Continued instability and apprehension despite dedicated rehab.
Not Sure Which Option Is Right for You?
A specialist evaluation will identify your specific structural anatomy, bone dimensions, and appropriate stabilization options.
Discuss Your Shoulder StabilityHear From Our Recovered Patients
Real stories of shoulder joint stabilization, confidence restoration, and active living at Sathya Sai Hospital.
 Verified Recovery
"After multiple dislocations, the stabilization treatment gave me full confidence in my shoulder joint again."
 Verified Recovery
"Clear explanation of my shoulder scan, precise treatment plan, and guided rehab. No more slipping sensations."
 Verified Recovery
"Compassionate doctors and modern OT infrastructure. I am back to work and overhead activities comfortably."
Why Choose Sathya Sai for Shoulder & Orthopaedic Care?
Located in KR Puram, Bengaluru, Sathya Sai Orthopaedic & Multispeciality Hospital provides dedicated shoulder and sports injury care, from clinical evaluation to arthroscopic stabilization and rehabilitation.
Consult an Orthopaedic & Shoulder Arthroscopy Specialist
Consult our experienced orthopaedic and sports medicine team at Sathya Sai Hospital.

Dr. Vimal Kumar K H
Orthopaedic specialist with dedicated sub-specialty training in shoulder care, sports injuries, arthroscopic Bankart stabilization and ligament reconstruction.
Book Appointment
Dr. Mahesh M N
CEO and Medical Director with over 20 years of clinical experience in complex joint reconstruction, trauma and spine surgery.
Consult with Team
Dr. Vijay M
Senior Trauma and Arthroplasty Surgeon with over 20 years of orthopaedic excellence in complex joint procedures.
Consult with TeamFrequently Asked Questions About Shoulder Instability
Clear, medically responsible answers to common patient questions regarding shoulder dislocation, Bankart lesions, surgery, and recovery.
What is shoulder instability?
Shoulder instability is a condition where the head of the upper arm bone (humeral head) repeatedly slips, subluxates partially, or dislocates completely out of the socket (glenoid), causing pain, apprehension, and loss of arm confidence.
Why does my shoulder keep dislocating?
Recurrent dislocations typically happen because the initial injury tore the stabilizing labrum (Bankart lesion), stretched the capsule, or chipped the bone rim, leaving the joint mechanically compromised so that subsequent episodes occur with less force.
What is a Bankart lesion?
A Bankart lesion is a detachment of the cartilaginous labrum and attached ligaments from the lower-front rim of the shoulder socket that frequently occurs after an anterior shoulder dislocation.
Does every shoulder dislocation require surgery?
No. First-time dislocations in older or less active patients are often successfully managed with immobilization, physical therapy, and muscle strengthening. Surgery is considered primarily for recurrent episodes, young contact athletes, or significant structural defects.
Can shoulder instability improve without surgery?
In selected patients—particularly those with mild subluxation or generalized joint laxity—dedicated rotator cuff and periscapular strengthening can improve dynamic muscular joint control and relieve symptoms without surgical stabilization.
What tests are used to diagnose shoulder instability?
Specialists perform physical maneuvers such as the Apprehension test, Relocation test, and Sulcus sign to assess laxity. These are corroborated by specialized X-rays and MRI or MR arthrography to inspect internal soft-tissue and bone integrity.
Do I need an MRI after a shoulder dislocation?
An MRI is often recommended when symptoms persist, in younger active patients with high recurrence risks, or when planning stabilization surgery to clearly visualize labral detachment, capsular injury, and bone impaction.
What is arthroscopic Bankart repair?
It is a minimally invasive keyhole procedure where a small camera and instruments are used to re-anchor the detached labrum back to the glenoid bone rim using tiny suture anchors, restoring the socket bumper.
What is a Hill-Sachs lesion?
A Hill-Sachs lesion is a dent or bone compression fracture on the back of the humeral head that occurs when it impacts the hard edge of the socket during an anterior dislocation.
Can bone loss affect treatment?
Yes. If repeated dislocations have worn away or chipped significant bone from the socket rim, a soft-tissue Bankart repair alone may have higher failure rates. In such cases, bone-block stabilization (such as a Latarjet procedure) may be evaluated.
How long does recovery take after shoulder stabilization?
Recovery is gradual. A sling is usually worn for 3 to 6 weeks to protect the repair, followed by guided mobility exercises, progressive strengthening, and eventual clearance for contact sports typically extending across several months based on functional criteria.
When can I return to the gym or sport?
Light conditioning and lower-body cardio start early. Non-contact training is phased in as strength normalizes. Return to overhead or contact sports (such as cricket, swimming, rugby, or martial arts) requires objective stability testing and specialist clearance.
Can physiotherapy help shoulder instability?
Yes. Dedicated physiotherapy strengthens the dynamic muscular stabilizers (rotator cuff and scapular muscles), improves neuromuscular coordination, and is essential both in conservative management and post-stabilization recovery.
Can shoulder dislocation happen again after surgery?
While surgical stabilization significantly restores joint stability, recurrence is still possible if high-energy trauma occurs, severe bone loss was present, or rehabilitation was not completed. Following post-operative guidelines protects the repair.
Have a question regarding your shoulder dislocation or scans?
Ask Our Orthopaedic TeamHas Your Shoulder Dislocated More Than Once?
Recurrent instability deserves a careful assessment of the shoulder and the structures that help keep it stable. A specialist can discuss whether rehabilitation, activity modification or stabilization treatment may be appropriate.
Request an Evaluation
Our team will call you to confirm appointment details.
Our orthopaedic coordination desk will contact you shortly.